A cellular and molecular basis for the selective desmopressin-induced ACTH release in Cushing’s disease patients: key role of AVPR1b receptor and potential therapeutic implications

Journal of Clinical Endocrinology and Metabolism, 07/25/2013  Review Article

Luque RM et al. – The study aims to determine, for the first time, whether desmopressin acts directly and exclusively on pituitary corticotropinoma cells to stimulate ACTH expression/release, and to elucidate the cellular and molecular mechanisms involved in desmopressin–induced ACTH increase in Cushing’s disease (CD).

The present results provide a cellular and molecular basis to support the desmopressin stimulation test as a reliable, specific test for the diagnosis and post–surgery prognosis of CD.

Furthermore, the data indicates that AVPR1b is responsible of the direct/exclusive desmopressin–stimulatory pituitary effects observed in CD, thus opening the possibility of exploring AVPR1b–antagonists as potential therapeutic tools for CD treatment.

~~~~~~~~

Abstract

  1. RM Luque1,#,
  2. A Ibáñez-Costa1,#,
  3. LM López-Sánchez1,
  4. L Jiménez-Reina2,
  5. E Venegas-Moreno3,
  6. MA Gálvez4,
  7. A Villa-Osaba1,
  8. AM Madrazo-Atutxa3,
  9. MA Japón5,
  10. A de la Riva6,
  11. DA Cano3,
  12. P Benito-López4,
  13. A Soto-Moreno3,
  14. MD Gahete1,
  15. A Leal-Cerro3,*and
  16. JP Castaño1,*

–Author Affiliations


  1. 1Department of Cell Biology, Physiology and Immunology University of Córdoba, Reina Sofía University Hospital, Instituto Maimónides de Investigación Biomédica de Córdoba (IMIBIC); CIBER Fisiopatología de la Obesidad y Nutrición (CIBERobn); 14014, Córdoba, Spain.

  2. 2Department of Morphological Sciences, University of Córdoba. Córdoba, Spain.

  3. 3Instituto de Biomedicina de Sevilla (IBiS), University Hospital Virgen del Rocío/Consejo Superior de Investigaciones Científicas/University of Seville and Endocrinology, Metabolism and Nutrition Unit, Virgen del Rocío University Hospital, Seville, Spain.

  4. 4Service of Endocrinology and Nutrition, Reina Sofía University Hospital, Instituto Maimónides de Investigación Biomédica de Córdoba (IMIBIC). Córdoba, Spain.

  5. 5Department of Pathology, Virgen del Rocio University Hospital, Seville, Spain.

  6. 6Service of Neurosurgery, Reina Sofía University Hospital Córdoba, Spain.
  1. Address all correspondence and requests for reprints to: Raúl M. Luque and Justo P. Castaño.Department of Cell Biology, Physiology and Immunology; Campus Universitario de Rabanales, Edificio Severo Ochoa (C6), Planta 3; University of Córdoba, E-14014 Córdoba, Spain. Phone:(34)-957218594. Fax: (34)-957218634. E-mails: raul.luque@uco.es; justo@uco.es.
  1. ↵# These authors have codirected this study.

Abstract

Context: Desmopressin is a synthetic agonist of vasopressin-receptors (AVPRs). Desmopressin stimulation test is employed in the diagnosis and post-surgery prognosis of Cushing’s disease (CD). However, the cellular and molecular mechanisms underlying the desmopressin-induced ACTH increase in CD patients are poorly understood.

Objective: 1) To determine, for the first time, whether desmopressin acts directly and exclusively on pituitary corticotropinoma cells to stimulate ACTH expression/release, and 2) to elucidate the cellular and molecular mechanisms involved in desmopressin-induced ACTH increase in CD.

Design: 8 normal-pituitaries (NPs), 23 corticotropinomas, 14 nonfunctioning-pituitary adenomas (NFPA), 17 somatotropinomas and 3 prolactinomas were analyzed for AVPRs-expression by qrtPCR. Primary cultures derived from corticotropinomas, NFPAs, somatotropinomas, prolactinomas and NPs were treated with desmopressin and ACTH-secretion/expression, [Ca2+]i-kinetics, AVPRs-expression and/or proliferative-response were evaluated. The relationship between AVPRs-expression and plasma adrenocorticotropin/cortisol levels obtained from desmopressin-tests was assessed.

Results: Desmopressin affects all functional parameters evaluated in corticotropinoma-cells but not in NPs or other pituitary-adenomas cells. These effects might be due to the dramatic elevation of AVPR1b expression levels found in corticotropinomas. In line with this notion, the use of an AVPR1b-antagonist completely blocked desmopressin-stimulatory effects. Remarkably, only AVPR1b-expression was positively correlated with elevated plasma adrenocorticotropin levels in corticotropinomas.

The present results provide a cellular and molecular basis to support the desmopressin stimulation test as a reliable, specific test for the diagnosis and post-surgery prognosis of CD. Furthermore, our data indicates that AVPR1b is responsible of the direct/exclusive desmopressin-stimulatory pituitary effects observed in CD, thus opening the possibility of exploring AVPR1b-antagonists as potential therapeutic tools for CD treatment.

Footnotes

  • ↵* These authors have codirected this study.

Full Text (PDF)

Laparoscopic Bilateral Transperitoneal Adrenalectomy For Cushing Syndrome

Surgical Laparoscopy, Endoscopy & Percutaneous Techniques, 07/16/2013  Clinical Article

Aggarwal S et al. –

Laparoscopic adrenalectomy is well established for treatment of adrenal lesions. However, bilateral adrenalectomy for Cushing syndrome is a challenging and time–consuming operation.

The authors report their experience of laparoscopic bilateral adrenalectomy for this disease in 19 patients. Laparoscopic bilateral adrenalectomy for Cushing syndrome is feasible and safe. It confers all the advantages of minimally invasive approach such as less postoperative pain, shorter hospitalization, lesser wound complications, and faster recovery.

The advantages of the laparoscopic approach have led to an earlier referral for bilateral adrenalectomy by endocrinologist in patients with failed pituitary surgery.


This article is available on PubMed

Cushing’s Disease – Rare Disease Quick Facts

cushings-diagnosis


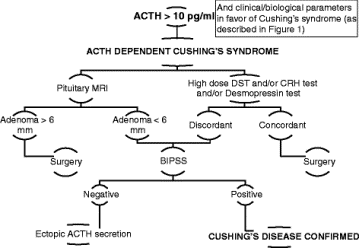
Cushing’s disease is a rare condition due to excess cortisol levels that result from a pituitary tumor secreting adrenocorticotropic hormone (ACTH), which stimulates cortisol secretion.  Cushing’s disease should not be confused with Cushing’s syndrome which is increased cortisol levels but that increase can be due to any number of factors. However, Cushing’s disease is the most common form of Cushing’s syndrome.

Symptoms

The symptoms related to Cushing’s disease and Cushing’s syndrome are the same, since both are related to an excess of cortisol. Also, symptoms vary extensively among patients and that, with the inherent fluctuation in hormone levels make it difficult to diagnosis both conditions.

Changes in physical characteristics of the body

  • Fullness and rounding of the face
  • Added fat on back of neck (so-called “buffalo hump”)
  • Easy bruising
  • Purplish stretch marks on the abdomen (abdominal striae)
  • Excessive weight gain, especially in abdominal region
  • Red cheeks
  • Excess hair growth on the face, neck, chest, abdomen and thighs

Changes in physiology/psychology

  • Generalized weakness and fatigue
  • Menstrual disorder
  • Decreased fertility and/or sex drive
  • High blood pressure that is often difficult to treat
  • Diabetes mellitus
  • Mood and behavior disorders

Diagnosis

The early stages of Cushing’s disease may be difficult to recognize. However, if it is suspected, diagnosis is generally a 2 stage process. First to determine if cortisol levels are high, and if so, why they are high.

Tests to confirm high cortisol levels:

  • 24-hour urine cortisol
  • Dexamethasone suppression test (low dose)

Tests to determine cause:

  • Blood ACTH level
  • Brain MRI
  • Corticotropin-releasing hormone test
  • Dexamethasone suppression test (high dose)
  • Petrosal sinus sampling

Treatment

Surgery

  • Most patients with Cushing’s disease undergo surgery to remove the pituitary adenoma offers.
  • If the tumor is isolated to the pituitary, cure rates of 80-85% are common.
  • If the tumor has spread to nearby organs, cure rates of 50-55% are common.

Medicine (approved orphan drugs)

Signifor (pasireotide)

  • Approved for patients with Cushing’s disease for whom pituitary is not an option or surgery has been ineffective.
  • Signifor is a somatostatin receptor agonist that leads to inhibition of ACTY secretion (and subsequently decreased cortisol levels).

Korlym (mifepristone)

  • Approved for patients with Cushing’s syndrome who have type 2 diabetes or glucose intolerance and have failed surgery (or not candidates for surgery).
  • Korlym is a glucocorticoid receptor antagonist which in turn blocks the effects of the high levels of cortisol in the body. Korlym is used to treat high glucose levels due to elevated cortisol.

Medicines used but not indicated for Cushing’s disease include

Mitoden

ketoconazole

Metyrapone

Etomidate

Radiation

  • Radiation therapy may be used in some patients and can be very effective in controlling the growth of these tumors.

Prognosis

In most cases, treatment can cure Cushing’s disease. If not treated properly, the chronic hypercortisolism can lead to excess morbidity and mortality due to increased cardiovascular and other risk factors.

For more information

National Library of Medicine, National Institute of Health

Cushing’s Disease Information (provided by Novartis Pharmaceuticals)


Images courtesy of the open access journal Orhanet Journal for Rare Diseases.  Castinetti et al. Orphanet J Rare Dis. 2012 7:41   doi:10.1186/1750-1172-7-41

– See more at: http://www.raredr.com/front-page-medicine/articles/cushings-disease-rare-disease-quick-facts-0

Pituitary tumor size not definitive for Cushing’s

By: SHERRY BOSCHERT, Family Practice News Digital Network

SAN FRANCISCO – The size of a pituitary tumor on magnetic resonance imaging in a patient with ACTH-dependent Cushing’s syndrome can’t differentiate between etiologies, but combining that information with biochemical test results could help avoid costly and difficult inferior petrosal sinus sampling in some patients, a study of 131 cases suggests.

If MRI shows a pituitary tumor larger than 6 mm in size, the finding is 40% sensitive and 96% specific for a diagnosis of Cushing’s disease as the cause of adrenocorticotropic hormone (ACTH)-dependent Cushing’s syndrome, and additional information from biochemical testing may help further differentiate this from ectopic ACTH secretion, Dr. Divya Yogi-Morren and her associates reported at the Endocrine Society’s Annual Meeting.

Pituitary tumors were seen on MRI in 6 of 26 patients with ectopic ACTH secretion (23%) and 73 of 105 patients with Cushing’s disease (69%), with mean measurements of 4.5 mm in the ectopic ACTH secretion group and 8 mm in the Cushing’s disease group. All but one tumor in the ectopic ACTH secretion group were 6 mm or smaller in diameter, but one was 14 mm.

Because pituitary “incidentalomas” as large as 14 mm can be seen in patients with ectopic ACTH secretion, the presence of a pituitary tumor can’t definitively discriminate between ectopic ACTH secretion and Cushing’s disease, said Dr. Yogi-Morren, a fellow at the Cleveland Clinic.

That finding contradicts part of a 2003 consensus statement that said the presence of a focal pituitary lesion larger than 6 mm on MRI could provide a definitive diagnosis of Cushing’s disease, with no further evaluation needed in patients who have a classic clinical presentation and dynamic biochemical testing results that are compatible with a pituitary etiology (J. Clin. Endocrinol. Metab. 2003;88:5593-602). The 6-mm cutoff, said Dr. Yogi-Morren, came from an earlier study reporting that 10% of 100 normal, healthy adults had focal pituitary abnormalities on MRI ranging from 3 to 6 mm in diameter that were consistent with a diagnosis of asymptomatic pituitary adenomas (Ann. Intern. Med. 1994;120:817-20).

A traditional workup of a patient with ACTH-dependent Cushing’s syndrome might include a clinical history, biochemical testing, neuroimaging, and an inferior petrosal sinus sampling (IPSS). Biochemical testing typically includes tests for hypokalemia, measurement of cortisol and ACTH levels, a high-dose dexamethasone suppression test, and a corticotropin-releasing hormone (CRH) stimulation test. Although IPSS is the gold standard for differentiating between the two etiologies, it is expensive and technically difficult, especially in institutions that don’t regularly do the procedure, so it would be desirable to avoid IPSS if it’s not needed in a subset of patients, Dr. Yogi-Morren said.

The investigators reviewed charts from two centers (the Cleveland Clinic and the M.D. Anderson Cancer Center, Houston) for patients with ACTH-dependent Cushing’s syndrome seen during 2000-2012.

ACTH levels were significantly different between groups, averaging 162 pg/mL (range, 58-671 pg/mL) in patients with ectopic ACTH secretion, compared with a mean 71 pg/mL in patients with Cushing’s disease (range, 16-209 pg/mL), she reported. Although there was some overlap between groups in the range of ACTH levels, all patients with an ACTH level higher than 210 pg/mL had ectopic ACTH secretion.

Median serum potassium levels at baseline were 2.9 mmol/L in the ectopic ACTH secretion group and 3.8 mmol/L in the Cushing’s disease group, a significant difference. Again, there was some overlap between groups in the range of potassium levels, but all patients with a baseline potassium level lower than 2.7 mmol/L had ectopic ACTH secretion, she said.

Among patients who underwent a high-dose dexamethasone suppression test, cortisol levels decreased by less than 50% in 88% of patients with ectopic ACTH secretion and in 26% of patients with Cushing’s disease.

Most patients did not undergo a standardized, formal CRH stimulation test, so investigators extracted the ACTH response to CRH in peripheral plasma during the IPSS test. As expected, they found a significantly higher percent increase in ACTH in response to CRH during IPSS in the Cushing’s disease group, ranging up to more than a 1,000% increase. In the ectopic ACTH secretion group, 40% of patients did have an ACTH increase greater than 50%, ranging as high as a 200%-300% increase in ACTH in a couple of patients.

“Although there was some overlap in the biochemical testing, it is possible that it provides some additional proof to differentiate between ectopic ACTH secretion and Cushing’s disease,” Dr. Yogi-Morren said.

In the ectopic ACTH secretion group, the source of the secretion remained occult in seven patients. The most common identifiable cause was a bronchial carcinoid tumor, in six patients. Three patients each had small cell lung cancer, a thymic carcinoid tumor, or a pancreatic neuroendocrine tumor. One patient each had a bladder neuroendocrine tumor, ovarian endometrioid cancer, medullary thyroid cancer, or a metastatic neuroendocrine tumor from an unknown primary cancer.

The ectopic ACTH secretion group had a median age of 41 years and was 63% female. The Cushing’s disease group had a median age of 46 years and was 76% female.

Dr. Yogi-Morren reported having no financial disclosures.

sboschert@frontlinemedcom.com

On Twitter @sherryboschert

From Famiiy Practice News

Johns Hopkins Pituitary Patient Day 2013

Johns Hopkins Pituitary Patient Day

Join us on Saturday, September 28, 2013, for the 5th Annual Patient Education Day at the Johns Hopkins Pituitary Center.

When: Saturday, September 28, 2013
Time: 9:30 a.m.
Location:
Johns Hopkins Mt. Washington Conference Center
5801 Smith Avenue
Baltimore, MD 21209
map and directions

Location of the pituitary gland in the human brain

Location of the pituitary gland in the human brain (Photo credit: Wikipedia)

Patient Education Day Agenda:
9:30 – 10:00 AM REGISTRATION
10:00 – 10:25 AM What is the pituitary gland, where it is located, what it does, and what can go wrong Gary Wand, MD
10:30 – 10:50 AM How pituitary tumors can affect your vision Prem Subramanian, MD, PhD
Vivek Patel, MD, PhD
10:50 – 11:10 AM Cushing disease journey: a patient’s perspective Stacey Hardy
11:15 – 11:40 AM Surgery for Pituitary tumors: from very tiny to very large Alfredo Quinones-Hinojosa, MD
Gary Gallia, MD, PhD
Alessandro Olivi, MD
11:40 – 12:00 PM Radiation therapy: when, why, and how Lawrence Kleinberg, MD
Kristen Redmond, MD
12:05 – 12:25 PM The medications you may be taking (new and old ones): what you need to know Roberto Salvatori, MD
12:30 – 1:25 PM Lunch
1:30 – 3:00 PM PM Round table sessions:
1) Medical therapy (Wand/Salvatori)
2) Surgical therapy (Quinones/Gallia/Olivi)
3) Radiation therapy (Redmond/Kleinberg/Lim)
4) Vision issues (Subramanian/Patel)

*This schedule is subject to change

Please R.S.V.P. by September 13, 2013, vie email (preferred) to PituitaryDay@jhmi.edu  or to Alison Dimick at 410-955-3921.

Reservations will be taken on a first-come, first-serve basis.